By continuing to use this site, you agree to our use of cookies as described in our Cookie Policy.
This website is intended for U.S. healthcare professionals only.
The Power of DHE
D.H.E. 45®, an established migraine and cluster headache therapy, has 80 years of clinical use1,2
DHE has the potential for a long duration of effect, so it’s usually quite long and associated with low recurrence.
-DR. STEWART TEPPER
DHE’s broad mechanism of action matters throughout an attack3
Broad receptor activity
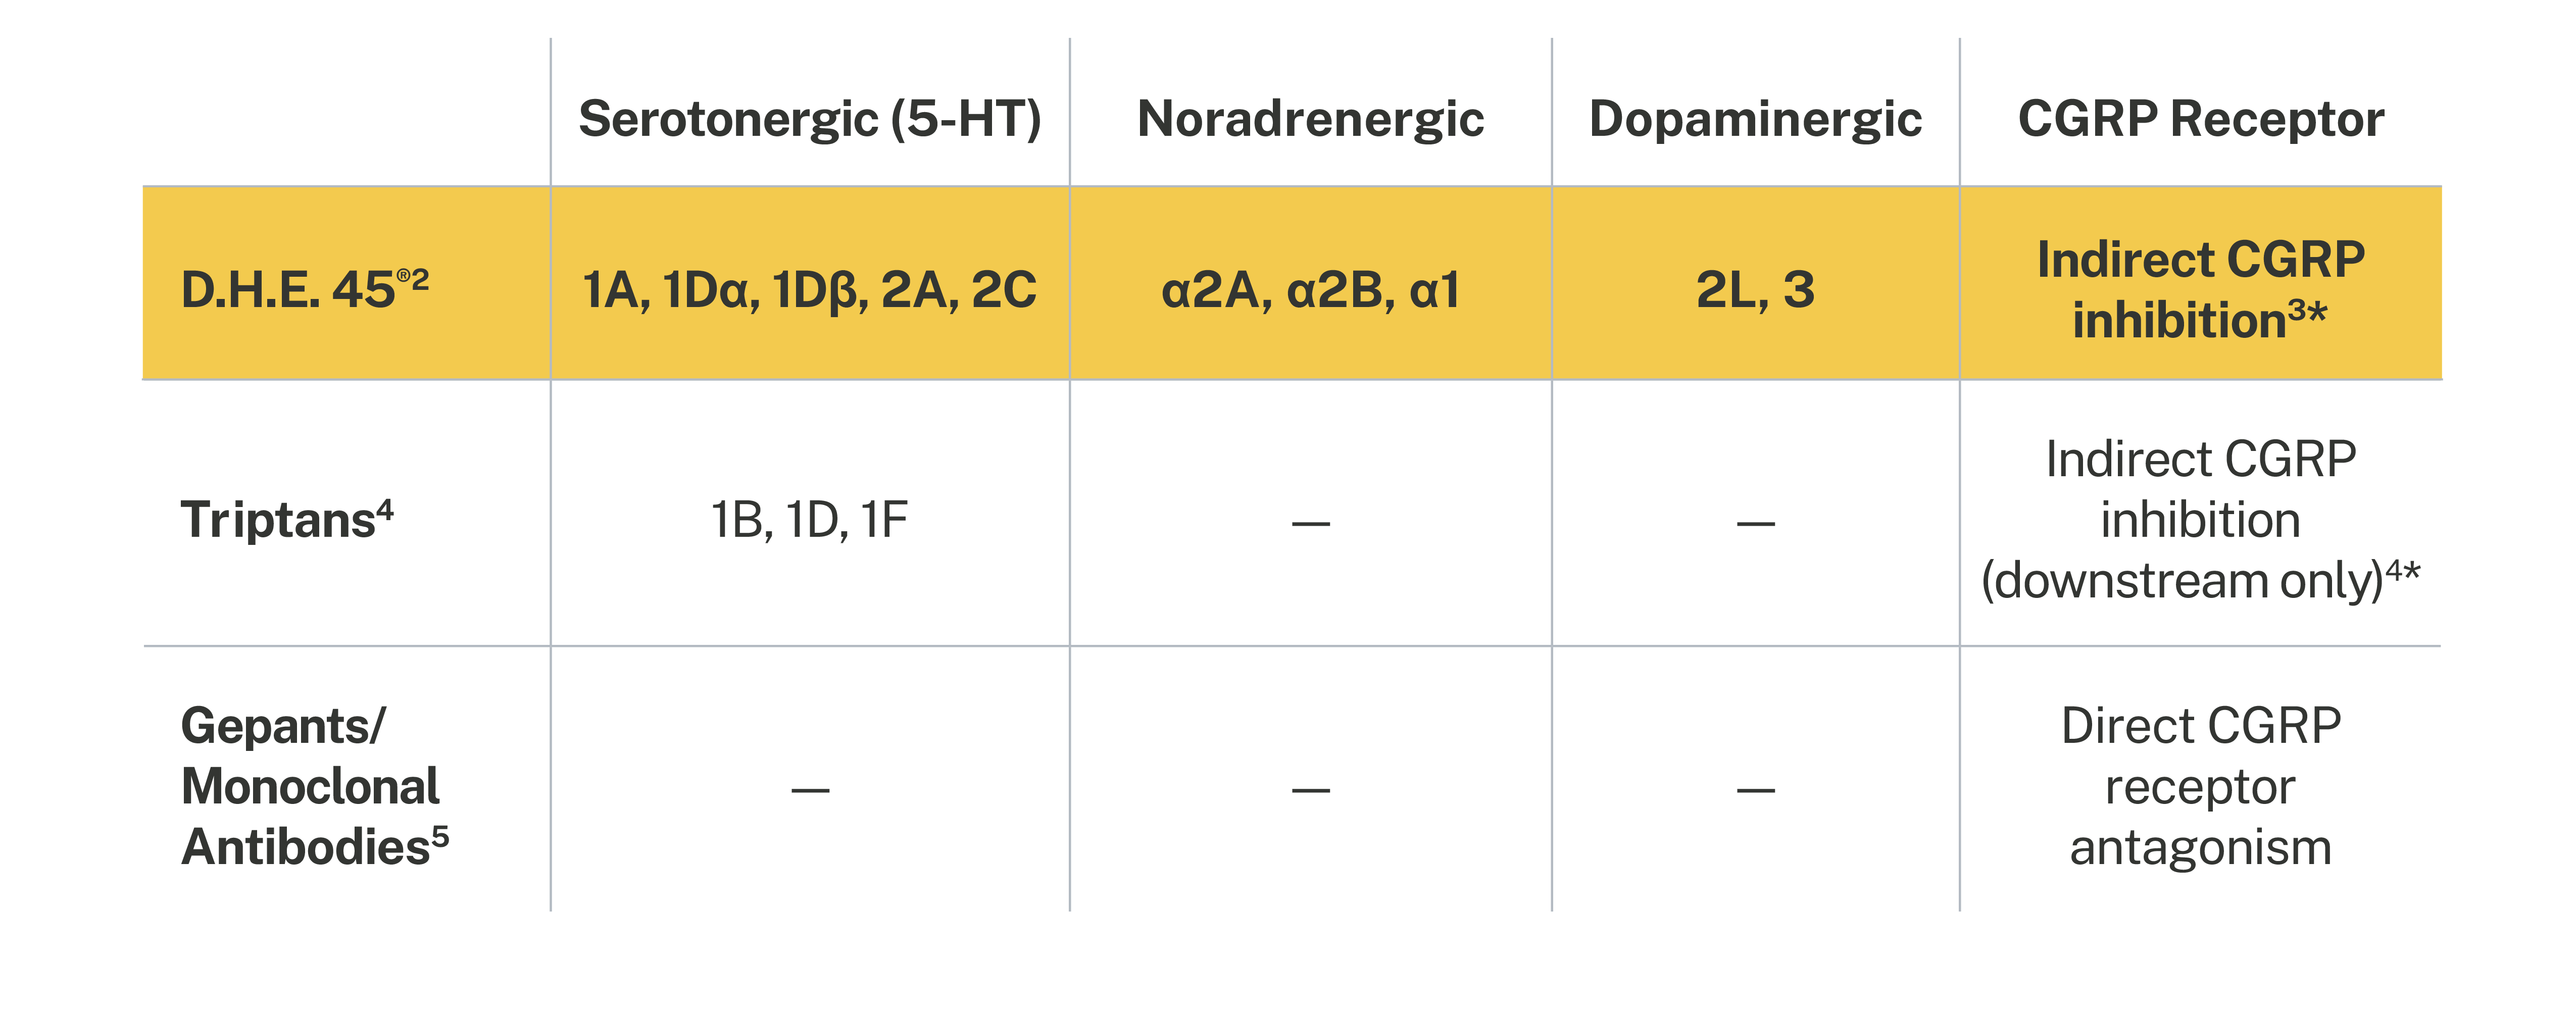
Regulates both neuropeptide release and vascular effects of already-released CGRP through a broad receptor profile (5-HT1B/1D, α-adrenergic, dopaminergic)3*
Broad receptor affinity distinguishes DHE from more selective acute treatment options
MECHANISM OF ACTION
Upstream
Limits further release of CGRP (and other neuropeptides) from trigeminal nerve terminals contributing to multiple factors causing pain3,6
Downstream
Activates 5-HT1B receptors to constrict blood vessels dilated by already-released CGRP3
Acts on receptors in the central nervous system and may reverse established central sensitization, interrupting the ongoing migraine attack6,7
Can be effective at any point during an attack and is often an effective treatment for patients with allodynia1,8
*The clinical significance of the receptor activity is unknown.9
Clinical studies over the past 80 years have also shown DHE to be effective in treating patients experiencing†:
†Findings were reported using studies with varied forms of DHE administration including intranasal, IV, and SC.1,7,9-11
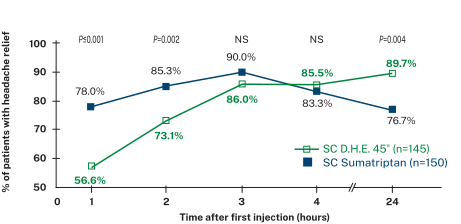
Study showed subcutaneous D.H.E. 45® effective in sustaining migraine pain relief12‡
PATIENTS WITH HEADACHE RELIEF12‡§
This data is based on a study of SC D.H.E. 45® vs. SC sumatriptan. Not studied in Brekiya autoinjector. Brekiya autoinjector contains DHE, the same active ingredient as D.H.E. 45®.
Significantly more patients achieved pain relief after 24 hours with SC D.H.E. 45® vs. SC sumatriptan (89.7% vs. 76.7%) (P=0.004)12‡§
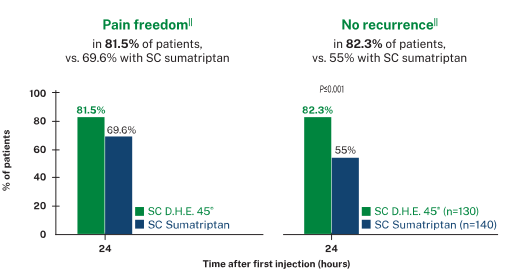
Study showed subcutaneous D.H.E. 45® effective in achieving pain freedom and reducing headache recurrence12||
PAIN FREEDOM AND HEADACHE RECURRENCE BY 24 HOURS12§‖
This data is based on a study of SC D.H.E. 45® vs. SC sumatriptan. Not studied in Brekiya autoinjector.
Brekiya autoinjector contains DHE, the same active ingredient as D.H.E. 45®.
Safety outcomes with SC D.H.E. 45® vs. SC sumatriptan12
No clinically significant differences in vital signs between treatments
No serious adverse events reported
All adverse events resolved spontaneously
SC D.H.E. 45® was associated with higher rates of nausea (15.9% vs. 5.9%) and vomiting (6.5% vs. 3.8%)
SC sumatriptan was associated with higher rates of chest pain (5.9% vs. 0.9%)
NS=not significant; SC=subcutaneous.
‡Pain relief was defined as a change from moderate or severe to mild or none. Sustained represents a duration of approximately 24-72 hours.12
§Data based on a randomized, double-blind trial of 295 adult patients with migraine with or without aura, experiencing moderate to severe head pain. Patients were given SC injections of either D.H.E. 45® (1 mg) or sumatriptan succinate (6 mg) into their lateral thigh and self-reported results from 0.5-24 hours after dose. Pain was rated on a 4-point scale as none, mild, moderate, or severe. Pain relief was defined as a change from moderate or severe at onset, to mild or none. 29.7% of patients in the D.H.E. 45® group and 15.3% of patients in the sumatriptan group received a second injection after 2 hours, with further rescue medication administered 1 hour after re-dose if needed. Main outcome measures were relief of head pain and recurrence of successfully treated headache.12
||Pain freedom defined as no pain at all at 24 hours post-dose; reported among patients in the efficacy analysis.12 No headache recurrence defined as no increase in pain severity from none or mild at least 2 hours after achieving pain relief.12
Based on a review of hospital records
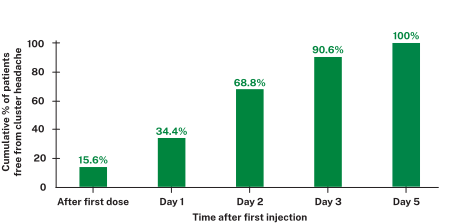
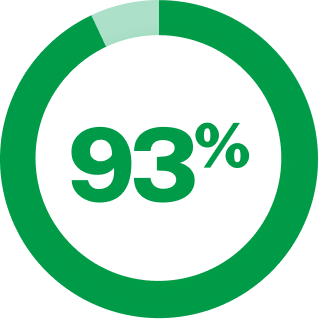
Intravenous D.H.E. 45® showed results in cluster headache13¶
PATIENTS WITH HEADACHE FREEDOM13¶
These data are based on a review of hospital records of IV D.H.E. 45®. Not studied in Brekiya autoinjector.
Brekiya autoinjector contains DHE, the same active ingredient as D.H.E. 45®.
of patients with episodic cluster headache were headache-free at 3 months13¶#
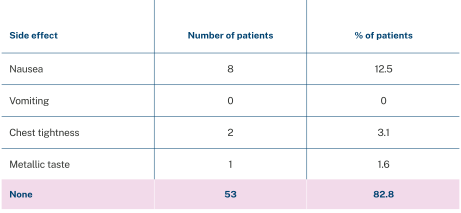
Safety evaluation in patients with cluster headache receiving intravenous D.H.E. 45®13#
SIDE EFFECTS (n=64)13#
¶Data based on a review of hospital records of 54 adult cluster headache patients (episodic and chronic) admitted to hospital on 64 occasions. Patients were given an initial dose of intravenous DHE, and subsequent doses based on response. Patients whose headaches improved were given further doses of IV DHE every 8 hours until they were headache-free for 24 hours. Patients whose headaches persisted were given an additional IV dose 1 hour after the first, followed by additional, larger IV doses every 8 hours until they were headache-free for 24 hours. All patients were then given 2-3 additional IV doses every 12 hours. Patients with nausea were treated with smaller doses. Subsequent breakthrough headaches were treated with self-administered intramuscular injections of DHE. Patients were given metoclopramide throughout their hospital stay.13
#This report also includes chronic cluster headache patients.
DHE can be used deep in a migraine attack when patients have central sensitization, when they have sensitivity to light and sensitivity to noise and nausea and that they’re at the peak of the migraine.
WARNING: PERIPHERAL ISCHEMIA FOLLOWING COADMINISTRATION WITH STRONG CYP3A4 INHIBITORS
Serious and/or life-threatening peripheral ischemia has been associated with the coadministration of dihydroergotamine with strong CYP3A4 inhibitors including protease inhibitors and macrolide antibiotics. Because CYP3A4 inhibition elevates the serum levels of dihydroergotamine, the risk for vasospasm leading to cerebral ischemia and/or ischemia of the extremities is increased. Hence, concomitant use of Brekiya with strong CYP3A4 inhibitors is contraindicated.
Indications
Brekiya is an ergotamine derivative indicated for the acute treatment of migraine with or without aura and the acute treatment of cluster headaches in adults.
Limitations of Use:
Brekiya is not indicated for the preventive treatment of migraine or for the management of hemiplegic migraine or migraine with brainstem aura.
Contraindications
Concomitant use of strong CYP3A4 inhibitors
Ischemic heart disease or coronary artery vasospasm
Uncontrolled hypertension, peripheral arterial diseases, sepsis, following vascular surgery, or severe hepatic or renal impairment
Concomitant use of other 5-HT1 agonists or ergotamine-containing or ergot-type medications within 24 hours
Hypersensitivity to dihydroergotamine, ergot alkaloids, latex, or any of the ingredients in Brekiya
Concomitant use with peripheral and central vasoconstrictors
Warnings and Precautions
Myocardial Ischemia and/or Infarction, Other Cardiac Adverse Reactions, and Fatalities: In patients with risk factors predictive of coronary artery disease, consider first dose administration under medical supervision with an electrocardiogram.
Cerebrovascular Adverse Reactions and Fatalities: Cerebrovascular hemorrhage, subarachnoid hemorrhage, and stroke have been reported; discontinue Brekiya if suspected.
Other Vasospasm Related Adverse Reactions: Brekiya may cause vasospasm or elevation in blood pressure. Discontinue if signs or symptoms of vasoconstriction develop.
Medication Overuse Headache: Detoxification may be necessary.
Preterm Labor: Advise pregnant women of the risk.
Fibrotic Complications: Pleural and retroperitoneal fibrosis have been reported following prolonged daily use of dihydroergotamine mesylate. Do not exceed the Brekiya dosing guidelines or use for chronic daily administration.
ADVERSE REACTIONS
Serious cardiac events (including fatal) that have been reported with dihydroergotamine mesylate injection use include coronary artery vasospasm, transient myocardial ischemia, myocardial infarction, ventricular tachycardia, ventricular fibrillation.
DOSAGE AND ADMINISTRATION
For subcutaneous injection only.
Recommended dosage is 1 mg administered subcutaneously as a single 1 mL autoinjector.
Do not exceed 3 mg (3 doses) in a 24-hour period.
Do not exceed 6 mg (6 doses) in a week.
Prior to initiation, a cardiovascular evaluation is recommended.
DRUG INTERACTIONS
Beta Blockers/Nicotine: May potentiate/provoke vasoconstriction.
Selective Serotonin Reuptake Inhibitors: Weakness, hyperreflexia, and incoordination may occur with coadministration.
USE IN SPECIFIC POPULATIONS
Pregnancy: Based on animal data, may cause fetal harm.
Lactation: Advise not to use during breastfeeding and for 3 days after the last dose.
References: 1. Silberstein SD, Shrewsbury SB, Hoekman J. Headache. 2020;60(1):40-57. doi:10.1111/head.13700 2. D.H.E. 45 [package insert]. Aliso Viejo, CA: Valeant Pharmaceuticals North America; 2008. 3. Silberstein SD, McCrory DC. Headache. 2003;43(2):144-166. doi:10.1046/j.1526-4610.2003.03034.x 4. Neeb L, Meents J, Reuter U. Neurotherapeutics. 2010;7(2):176-182. doi:10.1016/j.nurt.2010.03.003 5. Deen M, Correnti E, Kamm K, et al. J Headache Pain. 2017;18(1):96. doi:10.1186/s10194-017-0807-1 6. Goadsby PJ, Edvinsson L. Ann Neurol. 1993;33(1):48-56. doi:10.1002/ana.410330109 7. Tepper SJ. Headache. 2013;53(suppl 2):43-53. doi:10.1111/head.12184 8. Burstein R, Jakubowski M, Rauch SD. J Vestib Res. 2011;21(6):305-314. doi:10.3233/VES-2012-0433 9. Shafqat R, Flores-Montanez Y, Delbono V, Nahas SJ. J Pain Res. 2020;13:859-864. doi:10.2147/JPR.S203650 10. Brekiya [package insert]. Bridgewater, NJ: Amneal Pharmaceuticals LLC; 2025. 11. Silberstein SD, Kori SH. CNS Drugs. 2013;27(5):385-394. doi:10.1007/s40263-013-0061-212. Winner P, Ricalde O, Le Force B, Saper J, Margul B. Arch Neurol. 1996;53(2):180-184. doi:10.1001/archneur.1996.00550020092020 13. Mather PJ, Silberstein SD, Schulman EA, Hopkins MM. Headache. 1991;31(8):525-532. doi:10.1111/j.1526-4610.1991.hed3108525.x
TERMS, CONDITIONS, AND ELIGIBILITY CRITERIA
This card is not valid for prescriptions submitted for reimbursement to Medicare, Medicaid, Medigap, VA, DOD, or TriCare, or where prohibited by law; to other federal or state programs (including any state pharmaceutical assistance programs); or to private indemnity or HMO insurance plans that reimburse you for the entire cost of your prescription drugs. Patients may not use this card if Brekiya autoinjector is covered under their Medicare prescription drug plan or if they are Medicare-eligible and enrolled in an employer sponsored health plan or prescription drug benefit program for retirees.
This card is good for use only with a Brekiya autoinjector prescription at the time the prescription is filled by the pharmacist and dispensed to the patient.
Maximum reimbursement limits apply; patient out-of-pocket expenses may vary.
Amneal reserves the right to rescind, revoke, or amend this offer without notice.
Offer good only in the US.
Void if prohibited by law, taxed, or restricted.
The selling, purchasing, trading, or counterfeiting of this card is prohibited by law.
Are you a healthcare provider?
Are you a
healthcare provider?
The information contained in this website is intended for U.S. healthcare providers only. Click “Yes” if you are a U.S. healthcare provider.